

Robotic surgery is a platform. The outcome depends on what the surgeon does with it.
A robotic surgical system provides magnified three-dimensional vision and highly mobile instruments. But simply using a robot does not automatically produce a good prostatectomy.
A quality robotic radical prostatectomy requires the surgeon to make a series of decisions before, during and after surgery that balance three goals:
Cancer control + functional preservation + patient safety
The operation should be planned around the individual patient’s cancer rather than performed as a standardized sequence in every patient.
A high-quality RARP should aim for:
The cancer must be removed adequately, with appropriate attention to surgical margins and pathological staging.
Where oncologically appropriate, the surgical plan should aim to preserve structures contributing to urinary continence and sexual function.
Important structures in the deep pelvis need to be identified and protected whenever possible.
Blood loss, transfusion, complications, readmission and reoperation should be minimized.
The operation should be evaluated not only by what happens in the operating room, but by PSA, cancer control, continence, sexual function and quality of life over time.
The first critical step is not making the first incision.
It is understanding the cancer accurately.
Before surgery, the prostate cancer profile should be reviewed using the available clinical information.
This may include:
The objective is to answer:
Where is the cancer, how extensive is it, and what does that mean for the surgical plan?
MRI provides anatomical information.
Biopsy provides pathological information.
Neither should be considered in isolation.
Before surgery, the surgeon should understand:
The surgical plan can then be tailored to the individual cancer.
One of the most important principles of prostatectomy is:
Nerve preservation should follow oncological assessment — not replace it.
The surgeon should first determine how much tissue needs to be removed to achieve adequate cancer clearance.
Only then can the appropriate nerve-sparing strategy be planned.
This may result in:
The decision can differ between the two sides of the prostate.
Read more → Nerve-Sparing Robotic Prostatectomy
The prostate apex is an anatomically important region where cancer-control and functional considerations meet.
An overly aggressive dissection may compromise functional recovery.
An inadequate oncological dissection may increase the risk of a positive surgical margin.
The surgical objective is therefore: Precise apical dissection with appropriate cancer clearance while preserving functional anatomy whenever possible.
Urethral length and the external urinary sphincter are important considerations during apical dissection.
The urethra passes through the prostate and continues through the pelvic floor.
After the prostate is removed, the bladder has to be reconnected to the remaining urethra.
Where anatomy and cancer extent permit, preservation of functional urethral length can be an important component of the continence-preservation strategy.
This must be balanced against adequate removal of cancer at the apex.
The bladder neck is the junction between the bladder and prostate.
Depending on tumour location and anatomy, the bladder neck may be preserved or reconstructed after prostate removal.
The objective is to restore anatomy while maintaining adequate cancer clearance.
Bladder-neck management is therefore individualized rather than performed identically in every patient.
After prostate removal, the anatomical support structures around the urethra and bladder outlet can be reconstructed as part of the surgical technique.
Posterior reconstruction is one of the techniques that may be used to restore pelvic anatomy and support the vesicourethral anastomosis.
Its use and exact technique depend on individual anatomy and surgical judgement.
After prostate removal, the bladder and urethra must be reconnected.
This is the vesicourethral anastomosis.
The reconstruction should aim to be:
A well-constructed anastomosis is important for safe urinary recovery and helps reduce complications such as urinary leakage.
Pelvic lymph-node dissection is not required in every prostate cancer patient.
When indicated, the extent and anatomical template should be planned according to:
The aim is appropriate pathological staging without unnecessary morbidity.
Read more → Pelvic Lymph-Node Dissection in Prostate Cancer
The pelvis contains delicate nerves, vessels and supporting structures.
During robotic dissection, important principles include:
Robotic magnification and wristed instruments can facilitate precise dissection, but the surgeon’s anatomical knowledge and technique remain fundamental.
Blood loss is influenced by:
The aim is controlled dissection and haemostasis while avoiding unnecessary tissue injury.
In our analysed surgical series, average blood loss has been approximately 200 mL, with a transfusion rate of approximately 5%.
Not every prostatectomy is performed in an untouched pelvis.
Our practice includes patients with:
These patients may require modification of the usual surgical approach.
Previous procedures should therefore be identified during preoperative planning rather than discovered unexpectedly during surgery.
Robotic prostatectomy is performed deep within the pelvis.
The surgeon must understand the relationship between:
This becomes particularly important in patients with advanced disease or previous pelvic procedures.
A surgeon’s experience in complex pelvic oncology, not simply robotic console experience, can therefore be relevant when managing difficult prostate cancer cases.
Functional preservation should never result in leaving suspected cancer behind.
A surgeon may initially plan nerve preservation but modify the plan during surgery if the cancer requires wider excision.
Similarly:
The correct operation is the one that provides appropriate cancer clearance while preserving function where it is oncologically safe.
A positive surgical margin means that cancer cells are present at the inked edge of the removed surgical specimen.
It does not automatically mean that the cancer will recur.
However, positive margins can be associated with a higher risk of biochemical recurrence and need to be interpreted along with:
The aim of surgery is to achieve a negative surgical margin whenever possible without unnecessarily compromising functional preservation.
Dr Swati Shah has been performing robotic prostatectomy since 2013.
Her reported surgical experience includes:
627 – Robotic radical prostatectomies personally performed
650 – Total radical prostatectomies
~95% – Cases undergoing pelvic lymph-node dissection in the analysed series
~15 – Average lymph nodes retrieved
~10% – Positive surgical margins in the analysed series
~200 mL – Average blood loss
~5% – Transfusion rate
~2% – Major complications
~2% – Readmission
These figures represent surgeon-maintained clinical data and should be interpreted according to the specific cohort, definitions, case mix and duration of follow-up. Detailed oncological and functional outcomes are presented separately.
Urinary continence and erectile function are influenced by multiple factors.
Continence
Important factors include:
Erectile Function
Important factors include:
Therefore, a good operation should be considered part of a complete treatment and recovery pathway, rather than the end of treatment.
Surgical outcome is also influenced by postoperative management.
Our postoperative pathway includes attention to:
In our analysed series, average postoperative hospital stay has been approximately 2.8 days.
Individual recovery varies according to disease extent, procedure complexity and patient health.
A prostatectomy should not be considered successful simply because the patient leaves the hospital without a complication.
Long-term follow-up should include:
Cancer control
Functional recovery
Quality of life
This is why long-term outcomes are more meaningful than the number of robotic operations alone.
Read more → Life After Robotic Prostatectomy: Cancer & Functional Outcomes
Instead of asking only: “Do you perform robotic prostatectomy?”
patients may consider asking:
About experience
About cancer control
About functional outcomes
About complex cases
About follow-up
A transparent discussion is more useful than choosing a surgeon based only on the presence of a robotic system.
A quality robotic prostatectomy is not defined by:
“There is a robot.”
It is defined by the entire pathway:
Right patient selection
↓
Accurate staging
↓
Individualized surgical planning
↓
Appropriate cancer clearance
↓
Functional preservation when safe
↓
Safe reconstruction
↓
Low complication burden
↓
Rehabilitation
↓
Long-term oncological and functional follow-up
Dr Swati Shah’s prostate cancer practice has focused on the combination of:
Uro-oncology + Robotic Surgery + Pelvic Oncology + Functional Preservation
Her experience includes management of:
The aim is not to perform the same operation on every patient.
The operation is tailored to the cancer.
And within that oncological plan:
Every reasonable effort is made to preserve function.
Surgical Video
[FEATURED TECHNICAL RARP VIDEO] → Watch Robotic Prostatectomy Surgical Videos
Surgical Gallery
[FEATURED OPERATIVE shorts]
The robotic system provides a magnified, high-definition 3D view of the surgical field, allowing the surgeon to clearly identify delicate anatomical structures such as tiny blood vessels and important nerves. This enhanced visualization is particularly valuable during prostate surgery, where precise dissection is essential.
The system’s flexible wristed instruments can rotate and move with a range of motion that facilitates fine surgical movements in the confined pelvic space. This can help the surgeon perform accurate dissection while carefully working around critical structures.
The goal of robotic radical prostatectomy is to achieve complete cancer removal while, whenever oncologically appropriate, preserving important surrounding structures that contribute to urinary continence and sexual function.
रोबोटिक सिस्टम सर्जिकल क्षेत्र का मैग्निफाइड, हाई-डेफिनिशन 3D दृश्य प्रदान करता है, जिससे सर्जन छोटी रक्त वाहिकाओं और महत्वपूर्ण नसों जैसी नाजुक संरचनाओं को स्पष्ट रूप से पहचान सकते हैं। यह बेहतर विज़ुअलाइज़ेशन प्रोस्टेट सर्जरी में विशेष रूप से महत्वपूर्ण है, जहाँ सटीक तरीके से सर्जरी करना आवश्यक होता है।
सिस्टम के फ्लेक्सिबल रिस्टेड इंस्ट्रूमेंट्स कई दिशाओं में घूम और मुड़ सकते हैं, जिससे पेल्विस के सीमित स्थान में भी सर्जन को बारीकी से सर्जरी करने में मदद मिलती है। इससे महत्वपूर्ण संरचनाओं के आसपास सावधानीपूर्वक काम करते हुए सटीक डिसेक्शन किया जा सकता है।
रोबोटिक रैडिकल प्रोस्टेटेक्टॉमी का लक्ष्य कैंसर को पूरी तरह निकालना होता है। साथ ही, जहाँ कैंसर की स्थिति इसकी अनुमति देती है, वहाँ पेशाब पर नियंत्रण (urinary continence) और यौन कार्य (sexual function) में महत्वपूर्ण भूमिका निभाने वाली आसपास की संरचनाओं को सुरक्षित रखने का प्रयास किया जाता है।
The goal is to achieve a complete oncological resection while preserving as much functional anatomy as safely possible. Careful dissection can help maintain adequate urethral length, protect the external urinary sphincter, and preserve the nerves responsible for urinary and sexual function when oncologically appropriate.
Robotic surgery provides a magnified, high-definition three-dimensional view and wristed instruments that allow controlled, precise movements in this confined anatomical space. This can be particularly valuable during apical dissection, where even small differences in tissue planes and surgical technique can influence postoperative outcomes.
However, functional preservation should never compromise cancer clearance. The prostate and involved tissues must be removed completely with appropriate oncological margins based on the patient’s tumour characteristics.
Real Case
[FEATURED CASE — COMPLEX / T3 / PREVIOUS TURP / NERVE-SPARING] → View the complete case summary
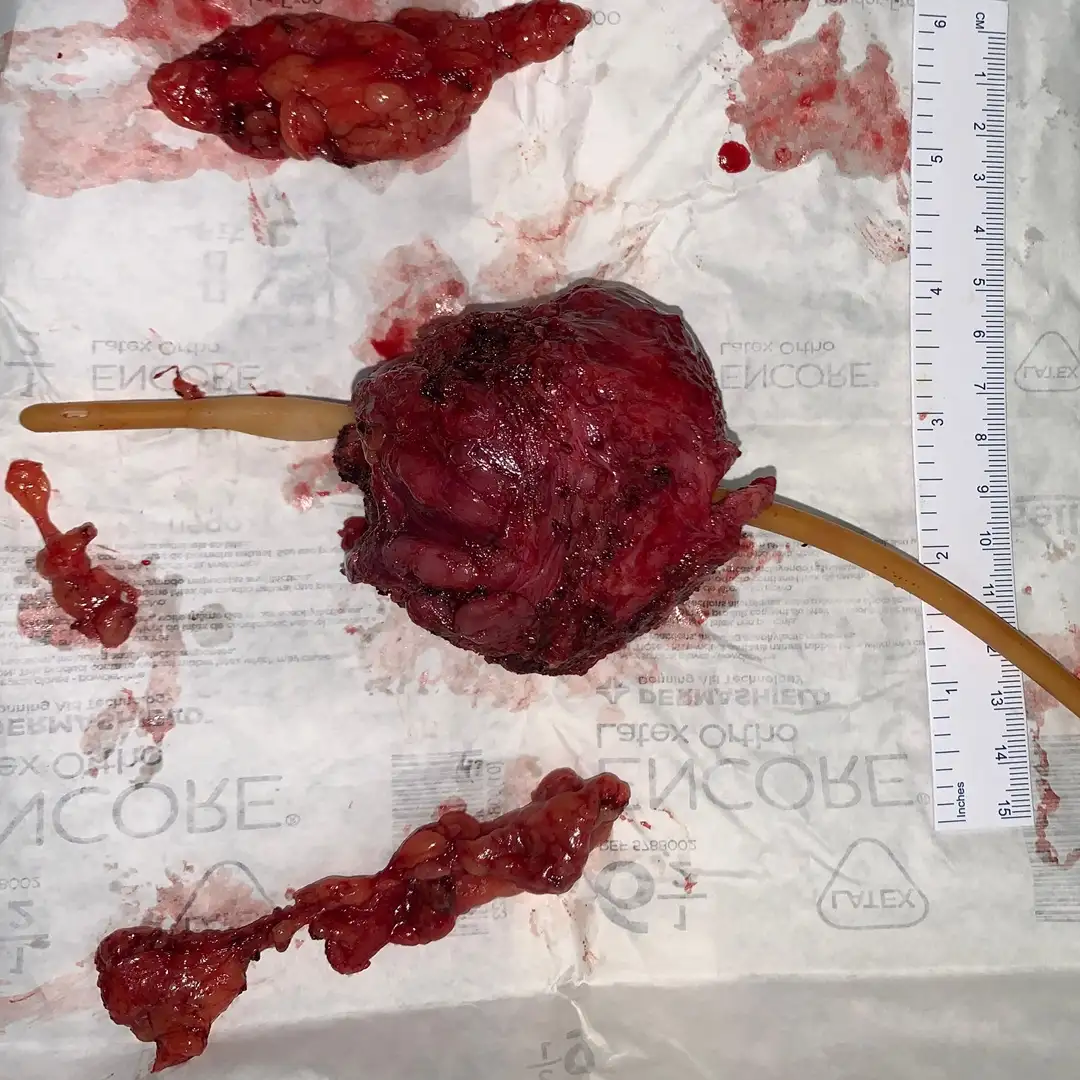
A 67-year-old male presented with urinary urgency and a significantly elevated PSA level of 144.92 ng/ml. Diagnostic imaging and biopsy confirmed an acinar adenocarcinoma, demanding an urgent and highly precise surgical intervention to prevent potential systemic spread while managing the high biochemical risk.
⦿ Robotic-Assisted Radical Prostatectomy and Lymphadenectomy
• Procedure: A minimally invasive radical prostatectomy was executed with unilateral neurovascular bundle preservation.
• Lymph Nodes: A total of 20 pelvic lymph nodes were successfully removed and staged.
• Safety: The surgery was completed with a very low blood loss of 150 ml.
• Cancer Clearance: Pathological examination confirmed negative surgical margins, indicating the complete removal of the tumor.
⦿ Full Oncological Clearance and Early Mobilization
The patient’s postoperative recovery was excellent, characterized by early mobilization and a stable discharge within a few days. Final histopathology confirmed a pT2N0 stage with zero lymph node involvement and no extraprostatic extension. Crucially, the patient achieved early urinary continence, returning to his routine daily activities without significant functional impairment or complications.
By utilizing robotic precision, we achieved complete cancer clearance despite the patient's high pre-operative PSA levels. This approach allowed for meticulous nerve preservation and reconstruction, which are vital for maintaining the patient's quality of life and ensuring a rapid return to normalcy.
Patient Experience
Read the experience of a patient treated for prostate cancer.
[FEATURED GOOGLE REVIEW] → Read Prostate Cancer Patient Reviews

The robotic platform provides magnified 3D visualization and articulated instruments, but outcomes depend on patient selection, surgeon technique, team experience and postoperative care. A robot by itself does not guarantee better cancer or functional outcomes.
There is no single step. Good outcomes result from appropriate staging and planning followed by precise oncological dissection, appropriate nerve and anatomical preservation, reconstruction, safe lymph-node management and postoperative follow-up.
No. Nerve preservation depends on the location and extent of cancer. Cancer clearance takes priority.
No. A positive margin is a pathological finding associated with an increased risk of recurrence, but its significance depends on the complete pathology and postoperative PSA. Further treatment is not automatically required in every patient.
Previous TURP can make the operation more technically challenging because normal tissue planes and anatomy may be altered. It does not automatically rule out robotic prostatectomy.
Selected patients with locally advanced or node-positive disease may undergo surgery as part of a multimodal treatment strategy. These decisions require individualized staging and multidisciplinary planning.
Blood loss varies with anatomy, prostate size, cancer extent, lymph-node dissection and surgical technique. In our analysed series, average blood loss has been approximately 200 mL.
Hospital recovery and return to normal activities vary. Urinary continence and erectile function may continue to improve over months after surgery.
A robotic prostatectomy is only as good as the planning, surgical technique, cancer control and follow-up behind it.
For each patient, the important questions are:
Is surgery appropriate?
How much cancer needs to be removed?
Can nerves and functional structures safely be preserved?
Are lymph nodes required?
How can complications be minimized?
How will cancer control and functional recovery be followed after surgery?
A high-quality prostate cancer programme should be able to answer all of these questions — not simply provide access to a robotic machine.
[REQUEST A PROSTATE CANCER SECOND OPINION]
[BOOK A CONSULTATION WITH DR SWATI SHAH]
What Is Robotic Radical Prostatectomy (RARP)?
Understand RARP, who may be suitable and what the operation involves.
Nerve-Sparing Robotic Prostatectomy
Understand how nerve preservation is planned and performed.
Pelvic Lymph-Node Dissection in Prostate Cancer
Understand when lymph nodes are removed and what pathological staging means.
Localized Prostate Cancer: Surgery vs Other Treatment Options
Compare surgery with active surveillance and radiation-based approaches.
Locally Advanced & Node-Positive Prostate Cancer: Where Does Surgery Fit?
Understand surgery within multimodal treatment.
Life After Robotic Prostatectomy: Cancer & Functional Outcomes
Explore PSA, cancer control, continence, erectile function and our analysed outcomes.
Swasth Parivar: twice a month, practical advice on recovery, diet and warning signs. No advertising. Stop any time.
Your number is used for these updates and for the clinic to reach you. It is never sold or passed on. To stop, reply STOP on WhatsApp.
